
New study shows breast tumors evolve in response to hormone therapy

Many breast tumors grow in response to female hormones, especially estrogen. Drugs that reduce estrogen levels in the body often are effective in reducing tumor size and preventing recurrence of the cancer. But some tumors become resistant to these therapies and continue to grow and spread.

A new analysis of breast tumors, before and after hormone-reduction therapy, reveals the extreme genetic complexity of these tumors and the variety of responses that are possible to estrogen-deprivation treatments. The findings also suggest that analyzing a single sample of the breast tumor is insufficient for understanding how a patient should best be treated.

The study, led by researchers at The McDonnell Genome Institute at Washington University School of Medicine in St. Louis and Baylor College of Medicine, appears Aug. 9 in the journal Nature Communications.

“Estrogen-receptor-positive breast cancers are not created equal,” said co-senior author Elaine R. Mardis, PhD, the Robert E. and Louise F. Dunn Distinguished Professor of Medicine and co-director of the McDonnell Genome Institute. “Each woman’s disease can have a range of responses to estrogen-lowering drugs. This study demonstrates that reducing estrogen levels in estrogen-receptor-positive breast cancer changes the genetics of the tumor, and these changes may be important for deciding how best to treat a patient after the surgical removal of the tumor.”

The researchers analyzed 22 breast tumors before and after four months of treatment with aromatase inhibitors, drugs commonly given to post-menopausal women with breast cancer. After menopause, the ovaries no longer produce estrogen, and aromatase inhibitors block the body’s remaining production of the hormone. Successful treatment reduces the size of a tumor before it is surgically removed, and the therapy has been shown to improve long-term outcomes for patients.

“In the post-treatment tumor samples, we found many new mutations or enrichment of mutations already seen in the pre-treatment samples,” said co-senior author Matthew J. Ellis, professor and director of the Lester and Sue Smith Breast Center at Baylor. “This means that under the environmental stress of the treatment, the tumors are spawning new sub-clones that subsequently can survive and grow despite therapy, and that is why we are having difficulty in the end treating estrogen-receptor-positive breast cancer. We found this result in the majority of tumors we studied.”

The majority of the tumors analyzed — 18 of 22 — had complex genetic landscapes and dynamic responses to hormone deprivation therapy, meaning that many of the gene mutations present in the tumors before and after treatment were different. For example, in one patient, certain mutations present in 92 percent of the initial tumor were totally absent in samples taken after four months of aromatase inhibitor therapy.

“The broad implication is that patients who undergo aromatase inhibitor therapy for several months prior to surgery should be re-evaluated immediately before their operation to determine how the tumor may have changed in response to the therapy,” Mardis said. “Such information can help indicate whether further estrogen suppression treatment is likely to contribute to a lower risk of relapse.”

The researchers analyzed only one tumor that had a complex but stable genetic landscape, meaning it was largely unchanged by aromatase inhibitor treatment. Another tumor had very simple and stable genetics before and after treatment. And two patient samples indicated evidence of two independent but intertwining tumors with separate genetic origins.

“It was surprising to find two ‘collision’ tumors in a group of only 22 patients,” said first author Christopher A. Miller, PhD, an instructor in medicine at Washington University. “This hints that collision tumors may be more common than we have previously realized. In these cases, estrogen suppression was the right approach for one of the tumors, but not the other, which limited the effectiveness of the treatment.”

“Our study also demonstrated that even single tumors can evolve in response to therapy very quickly,” Miller added. “This suggests that sequencing a tumor at diagnosis is not enough. Periodically scanning a tumor’s genome to understand how it is changing may ultimately help us evolve our treatment strategies to match.”

The study also reinforced past research suggesting that mutations in a gene called ESR1 are associated with resistance to aromatase inhibitor therapy, but the analysis did not identify any new genes that may also be responsible for conferring resistance to these drugs.

Study aims to find clues to breast cancer outcomes in African-American women

Scientists’ understanding of the genetic roots of breast cancer is based largely on research conducted in women of European ancestry.

That knowledge does little to help explain why African-American women with the disease are more likely to be diagnosed at younger ages and with more aggressive tumors than their white counterparts. They also die of breast cancer at higher rates.

Now, researchers at Washington University School of Medicine in St. Louis are launching a major study in African-American women with breast cancer to learn whether their genetic risks are influenced by the same mutations that affect white women or are altogether different mutations. Such information may lead to new ways to prevent or treat breast cancer in African-American women.

“We’ve had a revolution in genetic testing over the past 10 years,” said the study’s senior investigator, Laura Jean Bierut, MD, the Alumni Endowed Professor of Psychiatry. “We’ve been able to identify many gene variants that contribute to a variety of cancers, including breast cancer. But as you examine the data, you realize most of these studies have been done in populations of European ancestry and that we don’t understand very much about the genetic causes of cancer in other populations, particularly in African-American women.”

According to the National Cancer Institute, African-American women with breast cancer often are diagnosed with the disease at younger ages, and they have a higher incidence of a particularly aggressive form of breast cancer, called the triple-negative subtype, than women from other racial and ethnic groups.

“Better understanding of the genetics of the disease in African-American women could be very helpful in earlier diagnosis, prevention and treatment,” said co-investigator Foluso Ademuyiwa, MD, an assistant professor of medicine in the Division of Medical Oncology.

In this new study, the researchers will enroll African-American women who have had breast cancer, regardless of when their diagnoses occurred. Bierut, who serves as the principal investigator of several national genetic studies, has teamed with Ademuyiwa and other researchers at the Siteman Cancer Center at Barnes-Jewish Hospital and Washington University School of Medicine to analyze the participants’ DNA.

At the same time, the National Institutes of Health (NIH) is launching a study to investigate how genetic and biological factors contribute to breast cancer risk in black women. As part of that study, researchers will compare the genomes of African-American women with breast cancer to the genomes of black women who don’t have the disease and to the genomes of white women who do. That study will share specimens, data and resources from 18 previous studies.

The Washington University study will gather and analyze new DNA samples from African-American women diagnosed with breast cancer. The researchers will conduct brief surveys with study volunteers to learn about their risk factors for breast cancer, such as family history, hormonal treatments the women may have undergone, and the number of children each may have had. After each interview, study volunteers will provide the researchers with two saliva samples to be sent to one of two commercial genomics companies for sequencing.

The companies — Color Genomics and 23andMe Inc. — will test each woman’s DNA, and the researchers will provide every study participant with an opportunity to find out what the genetic testing determines about the risk factors for breast cancer each woman carries.

The researchers also will offer participants genetic counseling, and they will contact study subjects about three months after the initial survey to determine whether they have shared the findings with family members who may have similar genetic risks for breast cancer, and with their physicians.

“Testing has become so easy that we don’t even need to do a blood draw,” Bierut said. “With saliva samples, we can analyze a woman’s DNA and take a look at known genetic variants that contribute to breast cancer. We also expect to find other, previously unidentified genetic variants specific to African-American populations. Our main goal is to improve diagnosis and treatment for these women.”

The study’s initial phase will involve only women in the St. Louis area. For more information, or to volunteer for the study, call 314-286-1393 or e-mail [email protected].

Siteman Cancer Center unveils new, state-of-the-art mammography van

Mobile mammography services continue to move forward in the St. Louis region with unveiling of Siteman Cancer Center’s new mammography van.

Equipped with high-resolution 3-D digital technology, the van provides the same advanced imaging that patients receive at Siteman’s four St. Louis area mammography clinics. Washington University radiologists who specialize in breast imaging read all Siteman mammograms, whether the exam takes place in the van or at a clinic.

“Mammography is known to reduce a woman’s risk of dying from breast cancer by an estimated 30-40 percent or more,” said Catherine Appleton, MD, chief of breast imaging at Siteman Cancer Center at Barnes-Jewish Hospital and Washington University School of Medicine in St. Louis. “But it matters where you receive your mammogram. Our team of physicians specializes in comprehensive breast imaging, and our van delivers that lifesaving expertise to women throughout the region.”

The 40-foot van is the fourth in three decades for Siteman Cancer Center.

In 2015, the mammography van served nearly 4,000 women at more than 100 sites:

  • 1,287 women at 35 office parks and other corporate locations;
  • 1,239 women at 40 community locations, including Schnucks and Shop ‘n Save grocery stores and YMCAs; and
  • 1,369 medically underserved women through our outreach program at 30 additional sites throughout the area.

“Siteman Cancer Center celebrates a long history of providing world-class care to our patients, and that certainly includes women who come to us for their mammograms,” said Timothy J. Eberlein, MD, Siteman’s director. “Mammography is the best test for identifying breast cancer before it can be felt – when the cancer is more likely to be curable.”

3-D imaging, also called tomosynthesis, uses X-rays to create multiple images. Then a computer digitally recreates the breast, allowing the radiologist to page through the scans on a computer screen like pages in a book or on an iPad or Kindle.

“This technology allows us to essentially see through the breast, one millimeter at a time,” Appleton said. “This has been shown both to reduce false alarms and to help reveal more breast cancers.”

Each exam takes about 20 minutes, and the exam fee is billed to the patient, her insurance company or Medicare. Results are reported to the patient and her physician within seven to 10 days.

The National Comprehensive Cancer Network (NCCN), an alliance of 26 of the nation’s leading cancer centers, recommends yearly mammograms for women age 40 and older with an average risk of developing the disease.

The Siteman Cancer Center van is certified by the U.S. Food and Drug Administration and is sponsored in partnership with Washington University’s Mallinckrodt Institute of Radiology, whose board-certified radiologists review all digital mammography images.

To make an appointment, call 1-800-600-3606 toll-free. Women should bring their insurance card to the appointment. For those without insurance, assistance is available. Call 314-454-8466 for more information.

For more information about mammography van dates and locations, visit http://sitemanmammogram.wustl.edu.

Breast cancer vaccine shows promise in small clinical trial

A breast cancer vaccine developed at Washington University School of Medicine in St. Louis is safe in patients with metastatic breast cancer, results of an early clinical trial indicate. Preliminary evidence also suggests that the vaccine primed the patients’ immune systems to attack tumor cells and helped slow the cancer’s progression.

The study appears Dec. 1 in Clinical Cancer Research.

The new vaccine causes the body’s immune system to home in on a protein called mammaglobin-A, found almost exclusively in breast tissue. The protein’s role in healthy tissue is unclear, but breast tumors express it at abnormally high levels, past research has shown.

“Being able to target mammaglobin is exciting because it is expressed broadly in up to 80 percent of breast cancers, but not at meaningful levels in other tissues,” said breast cancer surgeon and senior author William E. Gillanders, MD, professor of surgery. “In theory, this means we could treat a large number of breast cancer patients with potentially fewer side effects.

“It’s also exciting to see this work progress from identifying the importance of mammaglobin-A, to designing a therapeutic agent, manufacturing it and giving it to patients, all by investigators at Washington University,” he added.

The vaccine primes a type of white blood cell, part of the body’s adaptive immune system, to seek out and destroy cells with the mammaglobin-A protein. In the smaller proportion of breast cancer patients whose tumors do not produce mammaglobin-A, this vaccine would not be effective.

In the new study, 14 patients with metastatic breast cancer that expressed mammaglobin-A were vaccinated. The Phase 1 trial was designed mainly to assess the vaccine’s safety. According to the authors, patients experienced few side effects, reporting eight events classified as mild or moderate, including rash, tenderness at the vaccination site and mild flu-like symptoms. No severe or life-threatening side effects occurred.

Although the trial was designed to test vaccine safety, preliminary evidence indicated the vaccine slowed the cancer’s progression, even in patients who tend to have less potent immune systems because of their advanced disease and exposure to chemotherapy.

“Despite the weakened immune systems in these patients, we did observe a biologic response to the vaccine while analyzing immune cells in their blood samples,” said Gillanders, who treats patients at Siteman Cancer Center at Barnes-Jewish Hospital and Washington University. “That’s very encouraging. We also saw preliminary evidence of improved outcome, with modestly longer progression-free survival.”

Of the 14 patients who received the vaccine, about half showed no progression of their cancer one year after receiving the vaccine. In a similar control group of 12 patients who were not vaccinated, about one-fifth showed no cancer progression at the one-year follow-up. Despite the small sample size, this difference is statistically significant.

Based on results of this study, Gillanders and his colleagues are planning a larger clinical trial to test the vaccine in newly diagnosed breast cancer patients, who, in theory, should have more robust immune systems than patients who already have undergone extensive cancer therapy.

“If we give the vaccine to patients at the beginning of treatment, the immune systems should not be compromised like in patients with metastatic disease,” Gillanders said. “We also will be able to do more informative immune monitoring than we did in this preliminary trial. Now that we have good evidence that the vaccine is safe, we think testing it in newly diagnosed patients will give us a better idea of the effectiveness of the therapy.”

Special glasses help surgeons ‘see’ cancer

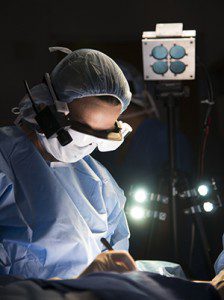
High-tech glasses developed at Washington University School of Medicine in St. Louis may help surgeons visualize cancer cells, which glow blue when viewed through the eyewear.

The wearable technology, so new it’s yet unnamed, was used during surgery for the first time Feb. 10, 2014 at Siteman Cancer Center at Barnes-Jewish Hospital and Washington University School of Medicine.

High-tech glasses developed at the School of Medicine help breast surgeon Julie Margenthaler, MD, visualize cancer cells in a patient.

Cancer cells are notoriously difficult to see, even under high-powered magnification. The glasses are designed to make it easier for surgeons to distinguish cancer cells from healthy cells, helping to ensure that no stray tumor cells are left behind during surgery.

“We’re in the early stages of this technology, and more development and testing will be done, but we’re certainly encouraged by the potential benefits to patients,” said breast surgeon Julie Margenthaler, MD, an associate professor of surgery at Washington University, who performed the operation. “Imagine what it would mean if these glasses eliminated the need for follow-up surgery and the associated pain, inconvenience and anxiety.”

The current standard of care requires surgeons to remove the tumor and some neighboring tissue that may or may not include cancer cells. The samples are sent to a pathology lab and viewed under a microscope. If cancer cells are found in neighboring tissue, a second surgery often is recommended to remove additional tissue that also is checked for the presence of cancer.

The glasses could reduce the need for additional surgical procedures and subsequent stress on patients, as well as time and expense.

Margenthaler said about 20-25 percent of breast cancer patients who have lumps removed require a second surgery because current technology doesn’t adequately show the extent of the disease during the first operation. “Our hope is that this new technology will reduce or ideally eliminate the need for a second surgery,” she said.

The technology, developed by a team led by Samuel Achilefu, PhD, professor of radiology and of biomedical engineering at Washington University, incorporates custom video technology, a head-mounted display and a targeted molecular agent that attaches to cancer cells, making them glow when viewed with the glasses.

Samuel Achilefu, PhD

In a study published in the Journal of Biomedical Optics, researchers noted that tumors as small as 1 mm in diameter (the thickness of about 10 sheets of paper) could be detected.

Ryan Fields, MD, a Washington University assistant professor of surgery and Siteman surgeon, plans to wear the glasses later this month when he operates to remove a melanoma from a patient. He said he welcomes the new technology, which theoretically could be used to visualize any type of cancer. “A limitation of surgery is that it’s not always clear to the naked eye the distinction between normal tissue and cancerous tissue,” Fields said. “With the glasses developed by Dr. Achilefu, we can better identify the tissue that must be removed.”

In pilot studies conducted on lab mice, the researchers utilized indocyanine green, a commonly used contrast agent approved by the U.S. Food and Drug Administration. When the agent is injected into the tumor, the cancerous cells glow when viewed with the glasses and a special light.

Achilefu, who also is co-leader of the Oncologic Imaging Program at Siteman Cancer Center and a professor of biochemistry and molecular biophysics, is seeking FDA approval for a different molecular agent he’s helping to develop for use with the glasses. This agent specifically targets and stays longer in cancer cells.

“This technology has great potential for patients and health-care professionals,” Achilefu said. “Our goal is to make sure no cancer is left behind.”

Viktor Gruev, PhD, assistant professor of engineering at WUSTL, and Ron Liang, PhD, of the University of Arizona, assisted with development of the glasses. WUSTL graduate students Suman Mondal, Shengkui Gao and Yang Liu and postdoctoral fellow Nan Zhu also played key roles.


High-tech glasses developed at the School of Medicine help breast surgeon Julie Margenthaler, MD, visualize cancer cells in a patient on Feb. 10. Here is real-time video of the lymph node removal, as seen by Margenthaler as she wore the eyewear. A florescent marker injected into the patient and special lighting made cancer cells glow blue when viewed with the technology. The lighter the shade of blue, the more concentrated the cancer cells are.

Some deadly breast cancers share genetic features with ovarian tumors

The most comprehensive analysis yet of breast cancer shows that one of the most deadly subtypes is genetically more similar to ovarian tumors than to other breast cancers.

The findings, published online Sept. 23 in Nature, suggest that most basal-like breast tumors and ovarian tumors have similar genetic origins and potentially could be treated with the same drugs, says the study’s co-leader Matthew J. Ellis, MD, PhD, the Anheuser-Busch Chair in Medical Oncology at Washington University School of Medicine in St. Louis. The other co-leader is Charles M. Perou, PhD, at the University of North Carolina.

Basal-like tumors account for about 10 percent of all breast cancers and disproportionately affect younger women and those who are African-American.

The new research is part of The Cancer Genome Atlas project, which brings together leading genetic sequencing centers, including The Genome Institute at Washington University, to identify and catalog mutations involved in many common cancers. The effort is funded by the National Institutes of Health (NIH).

“With this study, we’re one giant step closer to understanding the genetic origins of the four major subtypes of breast cancer,” says Ellis, who treats breast cancer patients at the Siteman Cancer Center at Barnes-Jewish Hospital and Washington University. “Now, we can investigate which drugs work best for patients based on the genetic profiles of their tumors. For basal-like breast tumors, it’s clear they are genetically more similar to ovarian tumors than to other breast cancers. Whether they can be treated the same way is an intriguing possibility that needs to be explored.”

Currently, for example, basal-like breast tumors often are treated like many other breast cancers, using anthracycline-based chemotherapy. But another of Ellis’s studies recently showed that women with basal-like tumors don’t benefit from these drugs, which also have severe side effects. At the very least, he says, the new data indicates that clinical trials should be designed to avoid the use of these drugs in basal-like tumors.

As part of the new research, a nationwide consortium of researchers analyzed tumors from 825 women with breast cancer. The scientists used six different technologies to examine subsets of the tumors for defects in DNA, RNA (a close chemical cousin of DNA) and proteins. Nearly 350 tumors were analyzed using all six technologies.

“By tying together those different data sets, we can build a story around the biology of each breast cancer subtype that is dictated by the genome, interpreted by the RNA and played out by the proteins at work inside each tumor,” says co-author Elaine Mardis, PhD, co-director of The Genome Institute. “These data can serve as a backdrop for other questions about how particular mutations affect survival or response to certain drugs.”

The study confirmed the existence of four main subtypes of breast cancer: Luminal A, luminal B, HER2 and basal-like. The latter includes most triple-negative breast tumors, so-named because they lack receptors for the hormones estrogen, progesterone or human epidermal growth factor 2 (HER2). These tumors often are aggressive and do not respond to therapies that target hormone receptors or to standard chemotherapies.

Across the four subtypes, mutations in only three genes – TP53, PIK3CA and GATA3 – occurred in more than 10 percent of patients’ tumors. But, the scientists found unique genetic and molecular signatures within each of the subtypes. Their findings add to the growing body of evidence suggesting that tumors should be cataloged and treated based on the genes that are disrupted rather than the location in the body.

In general, compared to the other subtypes, basal-like and HER2 tumors had the highest mutation rates but the shortest list of significantly mutated genes. These genes are thought to be major drivers of cancer progression. For example, 80 percent of basal-like tumors had mutations in the TP53 gene, which have been linked to poor outcomes. About 20 percent of the tumors also had inherited mutations in BRCA1 or BRCA2 genes, which are known to increase the risk of breast and ovarian cancer.

“This suggests that it only takes a few hits to key genes that drive cancer growth,” Mardis explains.

A high frequency of TP53 mutations also occurs in ovarian cancer, the researchers noted. Overall, the genetic profiles of basal-like and ovarian tumors were strikingly similar, with widespread genomic instability and mutations occurring at similar frequencies and in similar genes.

Finding new drug targets for basal-like breast tumors is critical, and the research suggests that patients with mutations in the BRCA genes may benefit from PARP inhibitors or platinum-based chemotherapy, which are already used to treat ovarian cancer.

By comparison, luminal cancers (which include estrogen receptor-positive and progesterone-receptor positive tumors) had the lowest mutation frequencies and longer lists of significantly mutated genes. This suggests defects in multiple genetic pathways can lead to the development of luminal breast cancers.

Most patients with luminal A cancer have good outcomes, and the most common mutation in that subtype occurred in PIK3CA, which was present in 45 percent of tumors. TP53 mutations only occurred in 12 percent.

Some patients with luminal B tumors do well but many experience recurrence years after treatment. Interestingly, the most common mutations in these tumors occurred in TP53 (linked to poor outcomes) and PIK3CA (linked to good outcomes), which may explain the disparate results seen in patients with this subtype.

“Now, we’re much closer to understanding the true origins of the different types of breast cancer,” Ellis says. “With this information, physicians and scientists can look at their own samples to correlate patients’ tumor profiles with treatment response and overall outcomes. That’s the challenge for the future – translating a patient’s genetic profile into new treatment strategies.”

This research is supported by the following grants from the National Institutes of Health (NIH): U24CA143883, U24CA143858, U24CA143840, U24CA143799, U24CA143835, U24CA143845, U24CA143882, U24CA143867, U24CA143866, U24CA143848, U24CA144025, U54HG003079, P50CA116201 and P50CA58223. Additional support was provided by the Susan G. Komen for the Cure, the Department of Defense through the Henry M. Jackson Foundation for the Advancement of Military Medicine, and the Breast Cancer Research Foundation.

Perou CM, Ellis MJ and The Cancer Genome Atlas network. Comprehensive molecular portraits of human breast tumours. Nature, Sept. 23, 2012.

Maggie, CU, Ellis MJ, Perou CM. Responsiveness of intrinsic subtypes to adjuvant anthracycline substitution in the NCIC. Clinical Cancer Research. Feb. 20, 2012.